
Innovative treatment for Diabetic Foot Ulcers
Diabetic Foot Ulcers can heal with our multi-targeting product AUP-16
WHAT ARE DIABETIC FOOT ULCERS (DFUs)?
DFUs are open sores or wounds that typically occur on the feet of people with diabetes. They represent one of the most challenging and serious complications of diabetes, particularly in those with poorly controlled blood sugar levels, neuropathy (nerve damage), and peripheral arterial disease (poor circulation). DFUs affect millions of people worldwide and can often lead to amputations or even death. Understanding the epidemiology, disease burden, and the pressing need for innovative treatments is important to understand this global health issue.
The lifetime risk of developing a Diabetic Foot Ulcer (DFU) is 19-34% for people with diabetes. The prevalence of DFUs is estimated to be 6.3% in people with diabetes worldwide. In Europe, approximately 5 out of 100 people with diabetes will develop a foot ulcer each year, and up to 25 out of 100 people may get one at some point in their lives. In the United States, between 4.5 to 10 out of 100 people with diabetes will develop a foot ulcer at any given time. These numbers show that DFUs are a common problem in urgent need for better treatments.


BURDEN AND COST OF DIABETIC FOOT ULCERS
DFUs are a major cause of morbidity and mortality in people with diabetes. The impact of DFUs goes beyond physical pain. They greatly increase the risk for amputation, leading to a significant disability and affecting people’s quality of life. In some cases, DFUs can even lead to death.
The economic burden of DFUs is also significant for individuals and health care systems. The total global cost of DFUs to society is estimated to be between 90-100 billion US $ per year. This includes both, the direct and indirect costs. The direct costs of DFUs include money spent on hospital visits, doctor visits, surgeries and ongoing care. The indirect costs include lost productivity, caregiving, and pain and suffering.
The cost of DFUs varies depending on the severity of the ulcer and the treatment required.
However, even a relatively simple ulcer can be expensive to treat e.g. the average cost of treating a non-healing DFU in the USA is close to 9,000 US $.
The indirect costs of DFUs can also be significant.
For example, a study in the United Kingdom found that the average cost of lost productivity due to a DFU was £5,000 per patient.
The total cost of DFUs is expected to increase in the coming years due to the rising prevalence of diabetes.
In 2021, there were an estimated 425 million adults diagnosed with diabetes worldwide. This number is expected to reach 578 million by 2030.
The global burden of DFUs is expected to increase in the coming years due to the rising prevalence of diabetes. There is a need for more research into the prevention and treatment of DFUs in order to reduce the associated morbidity, mortality, and economic burden.
CURRENT TREATMENTS FOR DIABETIC FOOT ULCERS
Some of the most common treatments for DFUs include:
• Debridement: This is the removal of dead tissue from the ulcer. It can be done surgically or with special dressings.
• Wound dressings: There are a number of different types of wound dressings available. They help to keep the ulcer clean and moist, which helps to promote healing.
• Offloading: This is used to help remove pressure on the ulcer due to body weight. It can be done with offloading shoes or total contact casting.
• Antibiotics: If the ulcer is infected, antibiotics may be prescribed.
• Surgery: In some cases, surgery may be necessary to remove the ulcer or to repair the damage to the foot.
Current treatments for DFUs face limitations that hinder the complete healing of the wound.
- Debridement: Even though removing dead tissue is crucial for wound healing, it only addresses one aspect of the problem.
- Wound dressings: Advanced dressings can create a moist environment for healing and prevent infection. However, they don’t address the root causes of the ulcer or promote healing from within.
- Offloading: This method effectively reduces pressure on the ulcer, but strict adherence can be difficult for patients, and it does not address circulatory problems that limit healing.
- Antibiotics: These are essential for fighting infections, but do not address any other factors that are essential for wound healing.
- Surgery: While surgery can remove infected tissue or improve blood flow, it is an invasive procedure with risks and may not be suitable for all patients.
AUP-16 MULTI-TARGET THERAPY FOR DIABETIC FOOT ULCERS
LEAD CLINICAL ASSET FOR CHRONIC WOUNDS
We believe that, when treating DFUs one needs to hit multiple targets to be disease-modifying. Very few companies or products can claim to be truly multi-target. Carefully designed and developed pharmaceutical products, such as our Advanced Therapy Medicinal Product (ATMP) AUP-16, will make the difference for patients. Our unique multi-target ATMP approach promotes the healing of the wound by promoting tissue regeneration and releasing active biological therapeutic agents within the wound itself.
AUREALIS THERAPEUTICS 4-IN-1 PRODUCT AUP-16
One Active Pharmaceutical Ingredient (API) product with the benefits of four therapeutics.
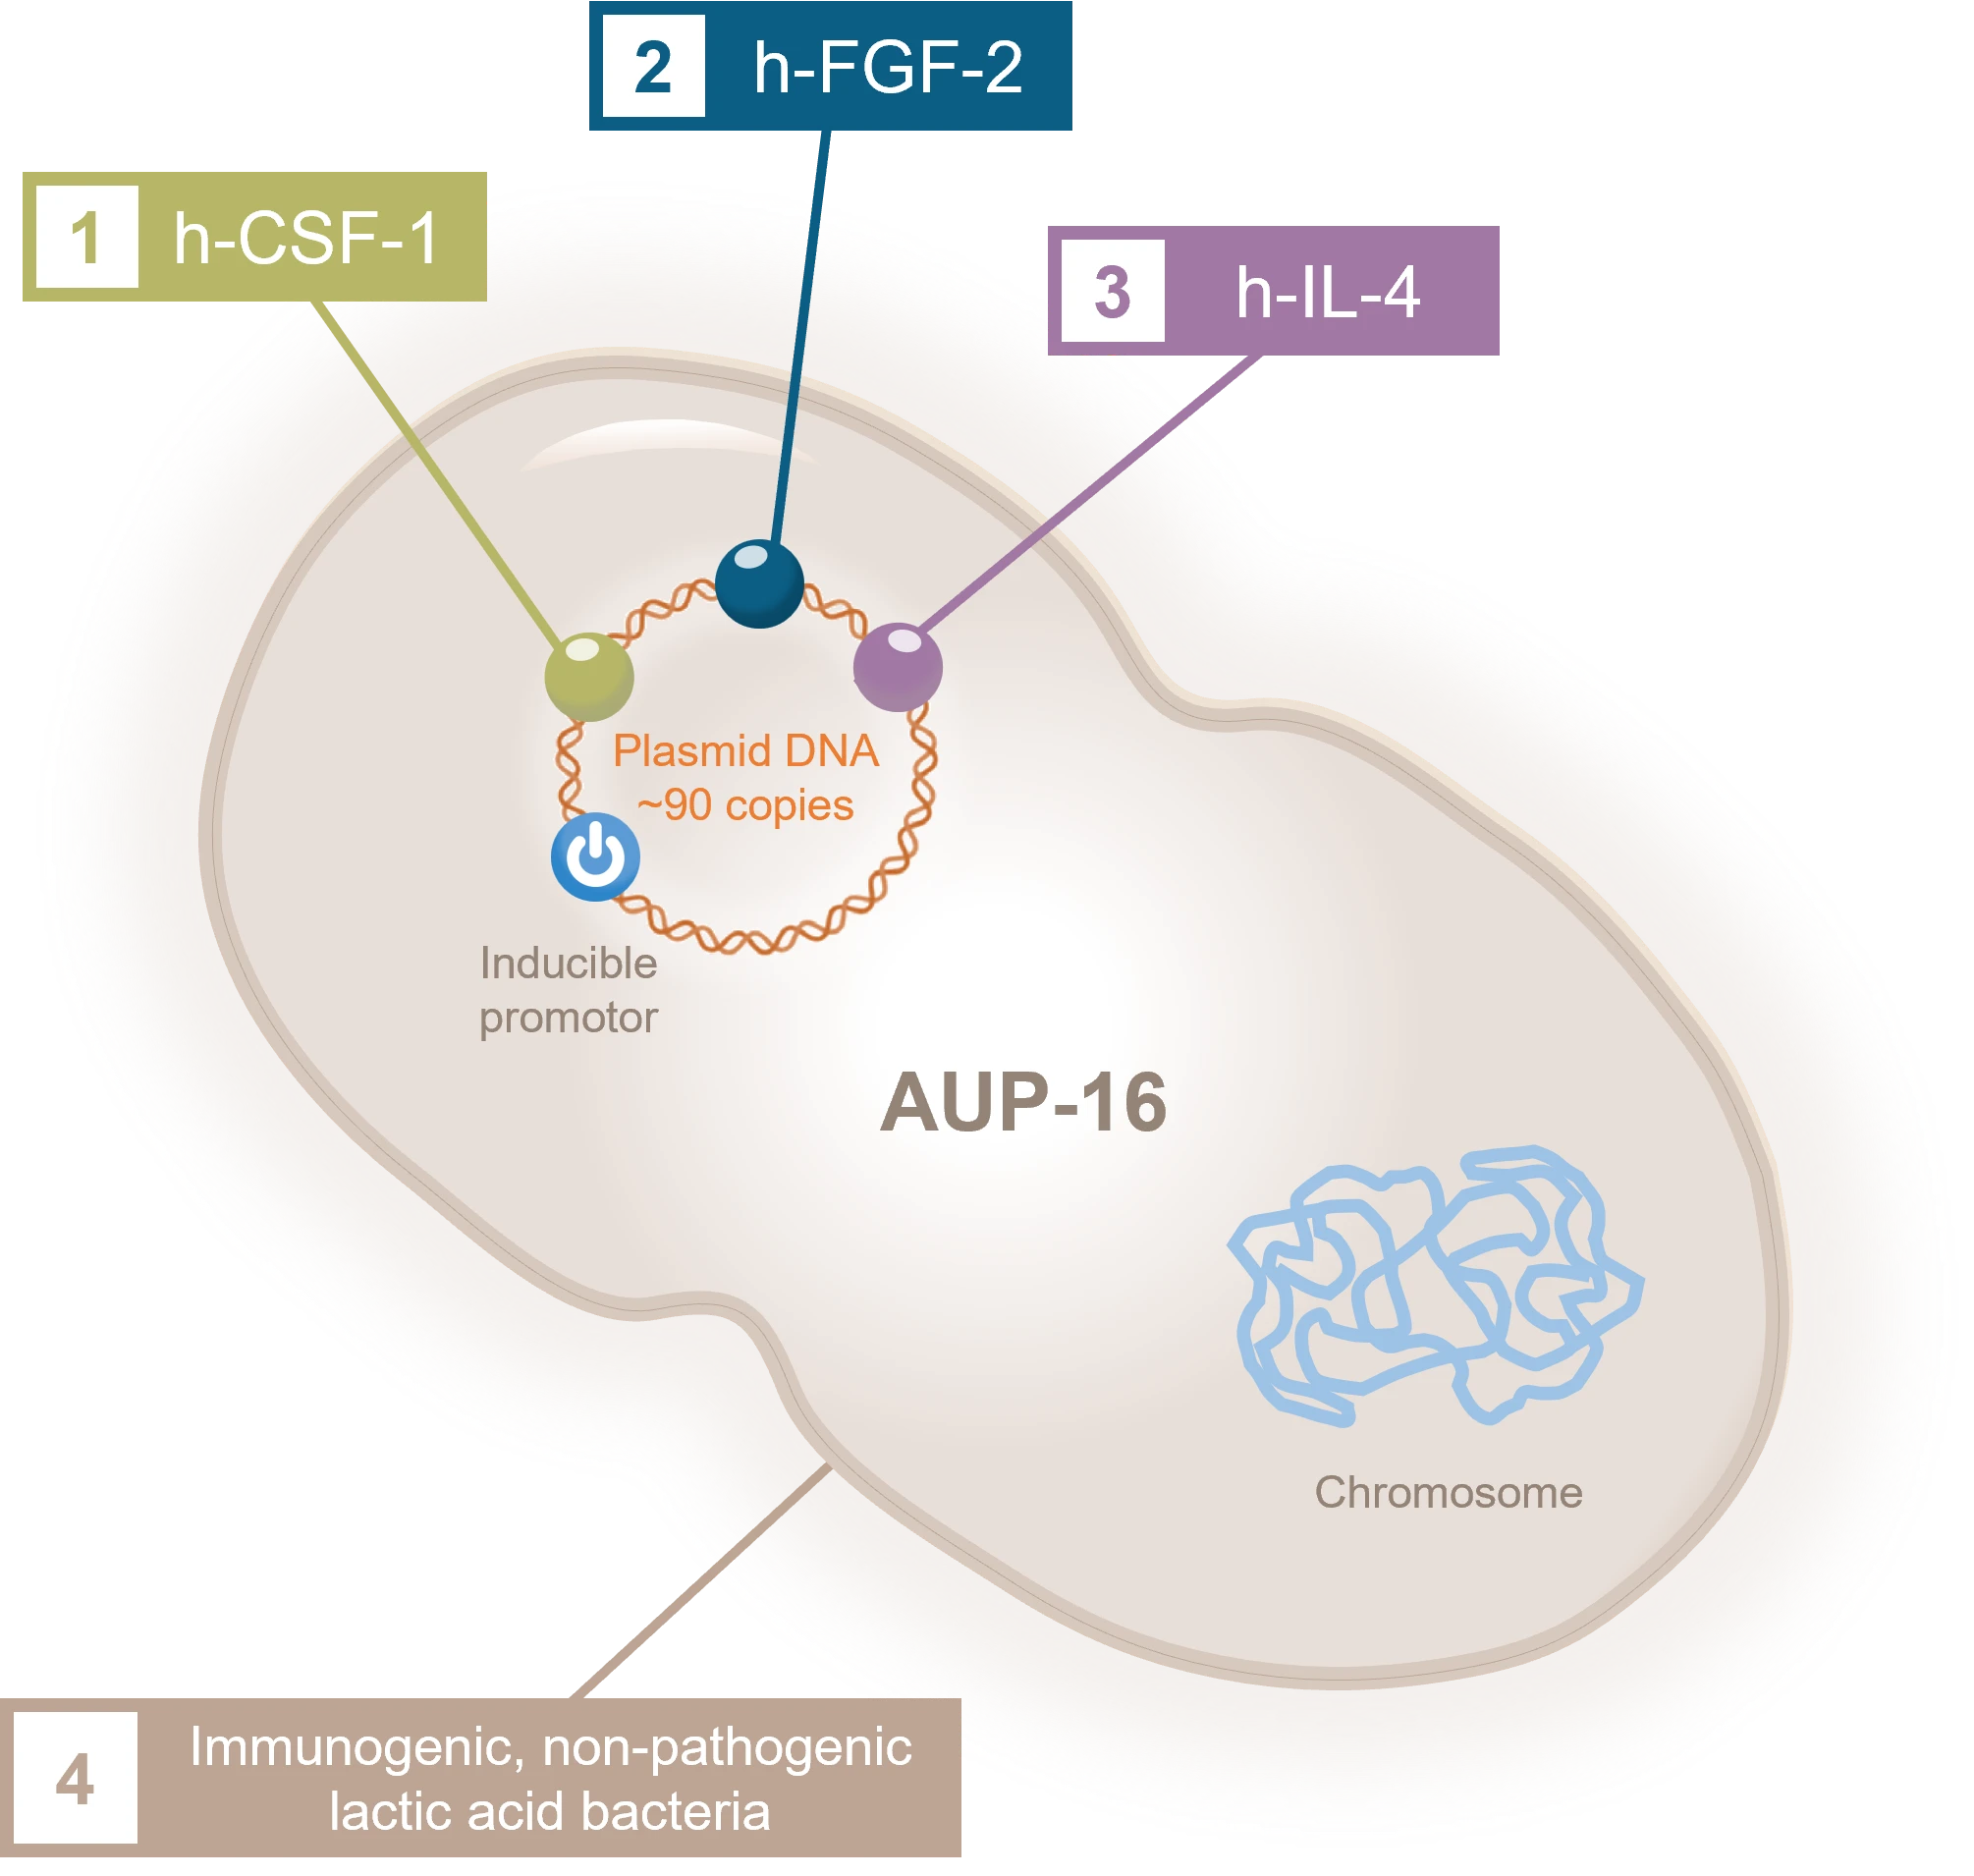
AUP-16 is a safe and effective recombinant live biotherapeutic product that features a patented active bacterial vector. AUP-16 includes four therapies in one product:
1. COLONY STIMULATING
FACTOR 1 (h-CSF-1)
A hematopoietic growth factor involved in the proliferation, differentiation, and survival of monocytes, macrophages, and bone marrow progenitor cells.
2. FIBROBLAST GROWTH FACTOR (h-FGF-2)
A clinically used growth factor and signaling protein involved in cell proliferation and tissue repair.
3. INTERLEUKIN 4
(h-IL-4)
A potent anti-inflammatory M2 cytokine that promotes regeneration.
4. LACTOCOCCUS
CREMORIS
A non-pathogenic bacteria that acts as a bioreactor in the tissue, producing human therapeutic proteins in the wound. AUP-16 takes advantage of the safe, living bioreactor to produce proteins FGF-2, IL-4 and CSF-1.
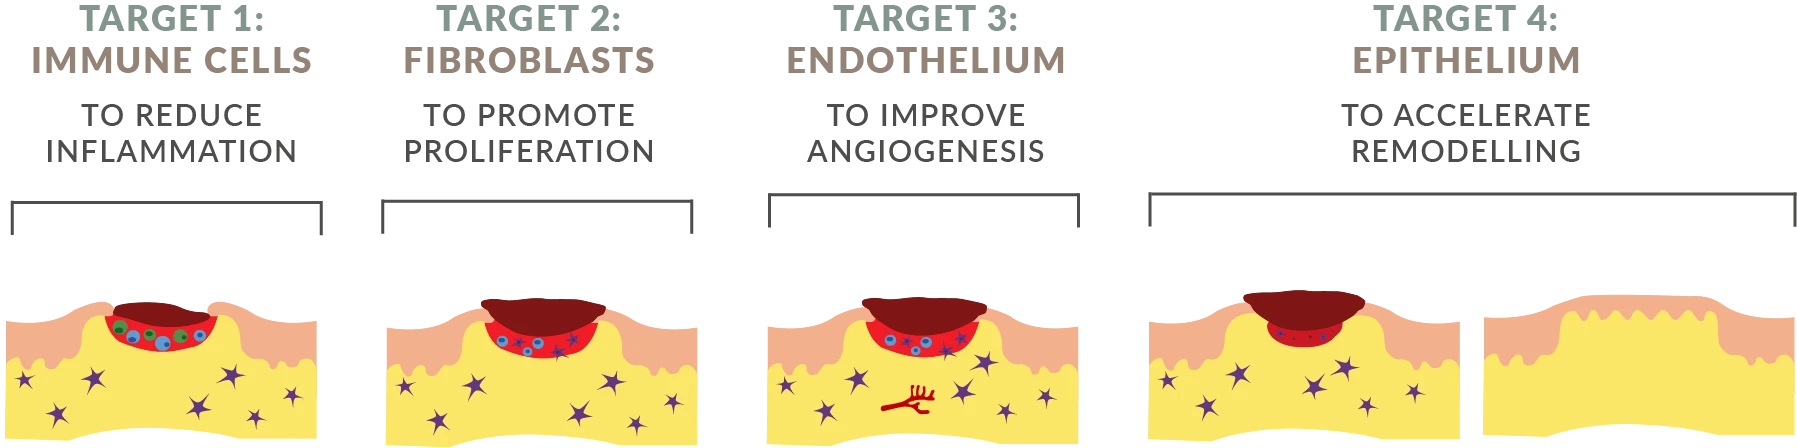
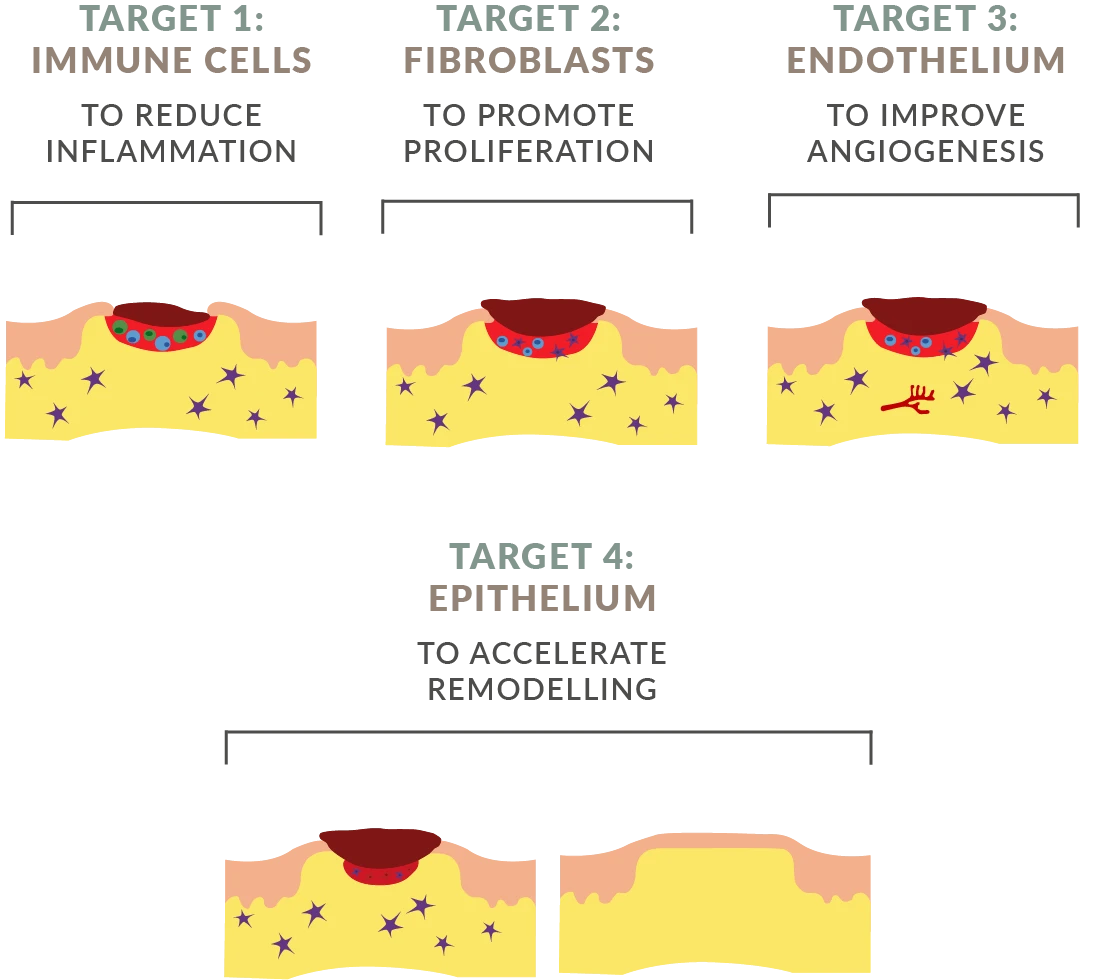
AUP-16 is a topical treatment created using a genetically modified lactococcus cremoris bacteria. AUP-16 promotes healing by producing three human therapeutic proteins that (1) improve cell activation and conversion to anti-inflammatory phenotype, (2) increase fibroblast proliferation, and (3) promote angiogenesis and granulation tissue formation.
The continuous production of the three human therapeutic proteins h-CSF-1, h-FGF-2 and h-IL-4 by the active vector lactococcus cremoris at the site of the wound, results in our unique 4-in-1 combination biological treatment which is provided as one API.
AUP-16 provides multi-therapy in one product, it is not a combination product. Thanks to its multi-therapy approach, AUP-16 is able to reduce inflammation promote proliferation and angiogenesis, and accelerate remodeling. All in one product.
Our therapy, AUP-16, is created under Good Manufacturing Practice (GMP) conditions and analyzed using state-of-the-art methods to ensure identity, potency, consistency, and safety.
AUP-16 has the power to accelerate and provide complete wound healing, avoiding amputations. This remarkable advancement is ideal for patients who only achieve partial response to wound care dressings and treatment of symptoms.
As opposed to the existing standard of care, AUP-16 promotes tissue regeneration in the wound to activate healing from within.
AUP-16 RECEIVED PRIME STATUS FROM THE EUROPEAN MEDICINES AGENCY
In February 2024, the Committee for Medicinal products for Human Use (CHMP) and the European Medicines Agency (EMA) have acknowledge that non-healing Diabetic Foot Ulcers (nhDFUs) are a potentially life-threatening condition with unmet need for novel therapies, and that AUP-16 has the potential to address this unmet medical need.
First Aurealis Therapeutics product candidate to receive PRIME designation by EMA for enhanced regulatory support facilitating the clinical development of multi-target cell and gene therapy candidate AUP-16 in the treatment of nhDFUs.
PRIME designation follows positive data for 16 patients from Phase-1 first-in-human study showing a dose-dependent improvement in wound closure, 67% and 83% wound closure at 3 and 6 months respectively, demonstrating the potential to address the unmet medical need in nhDFUs.
HIGHLIGHTS OF AUP-16
FOUR-IN-ONE
cell and gene therapy that stimulates endogenous tissue regeneration
BIOAVAILABLE
protein production at the site of the injury
TOPICAL APPLICATION
makes it easy to administer
SAFE
modified food-grade bacteria
LEARN ABOUT AUP-16 MODE OF ACTION
CLINICAL TRIALS IN DIABETIC FOOT ULCERS
AUP-16 phase 3 under preparation
PHASE 1 CLINICAL STUDY IN DFU (COMPLETED)
83% of the patients achieved complete healing. No healed ulcer recurred after 12 months follow-up.
In June 2022, we successfully completed the Phase 1 study (NCT04281992 and EudraCT 2018-003415-22) in non-healing Diabetic Foot Ulcer (nhDFU) patients with our lead product AUP-16. The last patient last visit (LPLV) was on 20th March 2023. Results were presented during European Wound Management Association (EWMA) 2023 conference in Milan and published on the Therapeutic Advances in Endocrinology and Metabolism peer-reviewed journal in November 2024.
Aurealis Therapeutics technology platform works in real life: non-healing diabetic wounds heal. Clinical results: 67% of patients reached complete healing at 20 weeks, up to 83% at the end of the study. No healed ulcer recurred after 12 months follow-up.
More details about our Phase 1 Clinical Study:
NIH National Library of Medicine record
More details about our Phase 1 Clinical Study:
EU Clinical Trials Register
PHASE 2 CLINICAL STUDY IN DFU (COMPLETED)
AUP-16 triples the complete wound closure rate in patients with chronic diabetic foot ulcers versus placebo.
In December 2025, we successfully completed the Phase 2 study (NCT06111183 and EudraCT 2022-502048-10-00) in non-healing Diabetic Foot Ulcer (nhDFU) patients with our lead product AUP-16. This was a multi-center, single-blinded, randomized, standard-of-care plus placebo-controlled study in patients with nhDFUs, conducted in Germany, Italy and Poland. The first DFU patient was dosed in August 2023 and the last patient last visit (LPLT) was on 17th October 2025. Blinded evaluator data was presented during European Wound Management Association (EWMA) 2026 conference in Bremen.
Clinical results: 3.2-fold increase in complete wound closure rate between placebo (20%) and AUP-16 administered twice weekly (64%), demonstrating a clinically and statistically significant advantage (+44% absolute increase, p value <0.05) in chronic DFUs with prior wound duration of more than three months.
More details about our DIAMEND Phase 2 Clinical Study:
NIH National Library of Medicine record
More details about our DIAMEND Phase 2 Clinical Study:
EU Clinical Trials Register
Peer-Reviewed Publications and Clinical Evidence
Peer-Reviewed Journal Articles
Conference Presentations and Posters
SCIENTIFIC PUBLICATIONS ABOUT AUP-16
Prof. Alberto Piaggesi presented the results of our DFU Phase-2 clinical study during an oral presentation at the European Wound Management Association (EWMA) Conference Bremen 2026 titled: Results of Phase-2 Randomized Controlled “DIAMEND” Study with Multi-targeting Cell & Gene Therapy AUP1602-C in Chronic Neuro-Ischemic Diabetic Foot Ulcers. Access the presentation.
Aurealis Therapeutics had a poster presented at the Symposium on Advanced Wound Care (SAWC) Charlotte 2026 titled: Final results of Phase-2 Randomized Controlled “DIAMEND” Study In Chronic Diabetic Foot Ulcer With Topical Multi-Target Cell & Gene Therapy AUP1602-C. Access the poster.
Aurealis Therapeutics had an abstract published and an e-poster presented at the European Wound Management Association (EWMA) Conference Barcelona 2025 titled: A randomized controlled Phase 2 trial to evaluate multi-factorial gene therapy AUP1602-C in the management of non-healing Diabetic Foot Ulcer. Access the abstract. Access the e-poster.
Aurealis Therapeutics published a scientific article in the Therapeutic Advances in Endocrinology and Metabolism peer-reviewed journal titled: Multi-target gene therapy AUP1602-C to improve healing and quality of life for diabetic foot ulcer patients: a phase I, open-label, dose-finding study. Access the scientific article.
Aurealis Therapeutics presented an abstract and a poster at ISPOR Health Economic Conference titled: A Markov model to determine the cost-effectiveness of a multi-targeting bacterial gene therapy (AUP-16) at healing a Diabetic Foot Ulcer when compared to the current standard of care. Access the abstract and the poster.
Aurealis Therapeutics presented a poster at the 14th International Symposium on Lactic Acid Bacteria titled: Multi-target bacterial gene therapy for chronic wounds and cancer. Access the poster.
Aurealis Therapeutics gave an oral presentation at the European Wound Management Association (EWMA) Conference Milan 2023 titled: 4-in-1 live biotherapeutic Gene Therapy Medicinal Product (GTMP) accelerates healing of Diabetic Foot Ulcers (DFUs): a first-in-human, phase 1 clinical study. Access the oral presentation.
Aurealis Therapeutics published a scientific article in the PLOS-One journal titled: 4-in-1 Combination therapy using Lactococcus lactis expressing three therapeutic proteins for the treatment of chronic non-healing wounds. Access the scientific article.
Aurealis Therapeutics presented a poster at the European Wound Management Association (EWMA) Conference Krakow 2018 titled: Therapeutic use of Lactococcus lactis bacteria to produce proteins locally in diseased tissues of chronic wounds. Access the poster.
SCIENTIFIC ADVISORY BOARD
diabetic foot ulcers

Professor of Medicine, University of Pisa
Former President of the European Wound Management Association (EWMA) and Founder/Treasurer of the Association of Diabetic Foot Surgeons (ADFS); pioneered diabetic foot conservative surgery with 5,000+ interventions and published 100+ peer-reviewed papers on diabetic foot management.


Professor of Surgery, University of Southern California; Founder & Co-Director SALSA
Most-published diabetic foot researcher (575+ peer-reviewed papers and 100+ book chapters); recipient of the inaugural Georgetown Distinguished Award for Diabetic Limb Salvage and the 2010 ADA Roger Pecoraro Award; youngest ever elected to Podiatric Medicine Hall of Fame (2008).


Senior Lecturer, Malmö University; Diabetes Nursing Specialist
Senior lecturer in nursing and diabetes care; research focused on diabetic foot management, patient education outcomes, and re-ulceration prevention; active member of EWMA Council and Foundation of European Nurses in Diabetes (FEND).
REFERENCES
- Armstrong DG, Boulton AJM, Bus SA. Diabetic Foot Ulcers and Their Recurrence. N Engl J Med. 2017;376(24):2367-75.
- Armstrong DG, Tan TW, Boulton AJM, Bus SA. Diabetic Foot Ulcers: A Review. JAMA. 2023;330(1):62-75.
- Chen P, Vilorio NC, Dhatariya K, Jeffcoate W, Lobmann R, McIntosh C, et al. Guidelines on interventions to enhance healing of foot ulcers in people with diabetes (IWGDF 2023 update). Diabetes Metab Res Rev. 2023:e3644.
- Hoffstad O, Mitra N, Walsh J, Margolis DJ. Diabetes, lower-extremity amputation, and death. Diabetes Care. 2015;38(10):1852-7.
- Kurkipuro J, Mierau I, Wirth T, Samaranayake H, Smith W, Karkkainen HR, et al. Four in one-Combination therapy using live Lactococcus lactis expressing three therapeutic proteins for the treatment of chronic non-healing wounds. PLoS One. 2022;17(2):e0264775.
- Margolis DJ, Kantor J, Berlin JA. Healing of diabetic neuropathic foot ulcers receiving standard treatment. A meta-analysis. Diabetes Care. 1999;22(5):692-5.
- McDermott K, Fang M, Boulton AJM, Selvin E, Hicks CW. Etiology, Epidemiology, and Disparities in the Burden of Diabetic Foot Ulcers. Diabetes Care. 2023;46(1):209-21.
- Meloni M, Izzo V, Giurato L, Lazaro-Martinez JL, Uccioli L. Prevalence, Clinical Aspects and Outcomes in a Large Cohort of Persons with Diabetic Foot Disease: Comparison between Neuropathic and Ischemic Ulcers. J Clin Med. 2020;9(6):1780.
- Rice JB, Desai U, Cummings AK, Birnbaum HG, Skornicki M, Parsons NB. Burden of diabetic foot ulcers for medicare and private insurers. Diabetes Care. 2014;37(3):651-8.
- Sun H, Saeedi P, Karuranga S, Pinkepank M, Ogurtsova K, Duncan BB, et al. IDF Diabetes Atlas: Global, regional and country-level diabetes prevalence estimates for 2021 and projections for 2045. Diabetes Res Clin Pract. 2022;183:109119.
- Walsh JW, Hoffstad OJ, Sullivan MO, Margolis DJ. Association of diabetic foot ulcer and death in a population-based cohort from the United Kingdom. Diabet Med. 2016;33(11):1493-8.
Frequently Asked Questions
01. Why do chronic wounds such as diabetic foot ulcers fail to heal?
Chronic wounds such as diabetic foot ulcers (DFUs) fail to heal because all four stages of normal wound healing are disrupted — inflammation resolution, tissue proliferation, angiogenesis, and epithelialization — trapping the wound in a persistent, destructive inflammatory state. Macrophages remain locked in a pro-inflammatory M1 phenotype instead of converting to regenerative M2, new blood vessel formation is suppressed, and fibroblast activity is impaired [1]. Because the dysfunction is multi-factorial, single-target treatments cannot restart the healing cascade on their own. Between 1–2% of the population in developed countries suffer from chronic wounds at any given time [2], and DFUs account for more than 60% of all non-traumatic lower-limb amputations [1].
References:
02. Why is complete wound closure the most important outcome in diabetic foot ulcer treatment?
Complete wound closure is the clinically decisive endpoint in diabetic foot ulcer care because an open ulcer is the entry point for infection and further complications leading to hospitalization, amputation or even death. A fully closed wound sharply lowers the risk of these complications and is the outcome that regulators such as the EMA and FDA recognize as meaningful. In the DIAMEND Phase 2 trial, final blinded evaluator data showed that AUP-16 administered twice weekly increased the complete wound closure rate 3.2-fold versus placebo (64% vs 20%) in the per-protocol population. By targeting durable, complete healing rather than incremental reductions in wound size, AUP-16 aims to change the trajectory of the disease.
03. What is the Aurealis platform?
The Aurealis Therapeutics platform is a modular synthetic biology cell and gene therapy platform based on Lactococcus cremoris — a non-pathogenic, food-grade lactic acid bacterium — genetically engineered to produce and release multiple human therapeutic proteins simultaneously at the disease site. It is the only platform in the world to have genetically engineered bacteria expressing three human therapeutic proteins simultaneously (for example h-CSF-1, h-FGF-2 and h-IL-4 in the case of AUP-16). Using an established bacterial backbone, a new customized product expressing 2–3 target proteins can be built in approximately six to ten weeks, making the platform applicable across chronic wounds, oncology, and inflammation.
04. How do Aurealis' products produce multiple therapeutic proteins from a single bacterium?
Each bacterium is engineered to carry approximately 90 copies of a multi-gene expression plasmid, turning every cell into a nanoscale bioreactor that continuously synthesizes and secretes multiple human proteins directly in the wound. The high plasmid copy number amplifies protein output per cell, and because production happens locally, therapeutic concentrations are sustained at the site of action without systemic exposure. All proteins produced are accepted by regulators as a single Active Pharmaceutical Ingredient (API), avoiding the complexity of a traditional multi-drug combination.
05. What is AUP-16 and what clinical stage is it in?
AUP-16 is Aurealis Therapeutics’ lead clinical asset — a genetically engineered Lactococcus cremoris that produces three human therapeutic proteins simultaneously: h-FGF-2 (fibroblast and vascular repair), h-IL-4 (macrophage conversion to regenerative M2 phenotype), and h-CSF-1 (immune microenvironment remodeling) [1, 2]. It is applied topically to chronic wounds as a single Advanced Therapy Medicinal Product (ATMP). As of May 2026, AUP-16 has completed Phase 2 development in diabetic foot ulcers (DIAMEND trial) with positive results [3], received PRIME designation from the EMA in February 2024, and is in preparation for a global pivotal Phase 3 trial.
References:
- doi:10.1371/journal.pone.0264775
- ClinicalTrials.gov. DIAMEND Phase 2 study: NCT06111183. clinicaltrials.gov/study/NCT06111183
06. What are the advantages of using lactic acid bacteria as a drug delivery vector?
Lactococcus cremoris has centuries of safe use in food fermentation, carries Qualified Presumption of Safety (QPS) status from EFSA and GRAS status from the FDA, and produces no endotoxins — making it inherently safer than gram-negative bacterial vectors or viral gene therapy vectors. Because the bacteria produce therapeutic proteins locally and continuously, they achieve sustained high concentrations at the wound without systemic side effects or the rapid degradation associated with single-dose protein application. Fermentation-based manufacturing of lactic acid bacteria is well established at industrial scale, enabling low cost of goods — a critical factor for broad patient access.
References:
07. What results has AUP-16 shown in clinical trials for diabetic foot ulcers?
In the completed Phase 1 study, 67% of patients with non-healing diabetic foot ulcers achieved complete wound closure at 20 weeks with the recommended Phase 2 dose, up to 83% at the end of the study, with zero recurrences during follow-up [1]. In the Phase 2 DIAMEND randomized controlled trial (64 patients, 10 sites across Germany, Italy, and Poland), AUP-16 tripled the complete wound closure rate versus placebo — 64% vs. 20% (p < 0.05) in the Per Protocol population — and wound area remaining at 20 weeks was 7.8 times lower in the AUP-16 group [2].
References:
08. What peer-reviewed publications support Aurealis' technology platform?
The Aurealis Therapeutics technology platform is supported by peer-reviewed journal articles, clinical study publications, and conference presentations at leading medical societies including EWMA and ASCO.
The full and up-to-date publication list is available at: aurealistherapeutics.com/pipeline-and-science/#publications.
09. How does multi-target gene therapy differ from single-target wound treatments?
Single-target treatments — including growth factor products, wound dressings, negative pressure therapy, and skin substitutes — each address only one aspect of the wound healing process, leaving the other disrupted pathways untreated [1]. Aurealis Therapeutics’ 4-in-1 platform simultaneously targets chronic inflammation (via IL-4-driven M2 macrophage conversion), angiogenesis and granulation tissue formation (via FGF-2), and immune microenvironment remodeling (via CSF-1) — all delivered as a single API [1, 2]. The clinical impact of this approach was demonstrated directly in the DIAMEND Phase 2 trial: AUP-16 achieved a 3.2-fold higher complete wound closure rate than placebo plus standard of care [3].
References:
- doi:10.1371/journal.pone.0264775
- doi:10.1177/20420188241294134
- Aurealis Therapeutics. DIAMEND Phase 2 results press release. December 4, 2025. aurealistherapeutics.com
